Cemento-osseous dysplasia (COD) is a benign jawbone condition that is common in middle-aged Black women. A University of Tennessee-led six-year review of 191 cases found that most COD patients were African American and female.
Why COD is so prevalent among older Black women is unknown, but researchers hypothesize COD prevalence could trace back to hormonal imbalances.
Because cemento-osseous dysplasia can resemble other jaw lesions on an X-ray, and the most reported symptom is pain, asymptomatic patients may undergo unnecessary biopsy or surgery in search of answers. Recent research emphasizes that, for asymptomatic patients, it’s best to monitor the condition and maintain dental health, reserving intervention for symptomatic or infected lesions. Clinicians should look for these diagnostic clues for COD to know when referral or biopsy is warranted.
COD is a benign condition in which fibrous tissue and hard, bone-like material replace parts of the normal jawbone. There are three types of COD: periapical, focal, and florid.
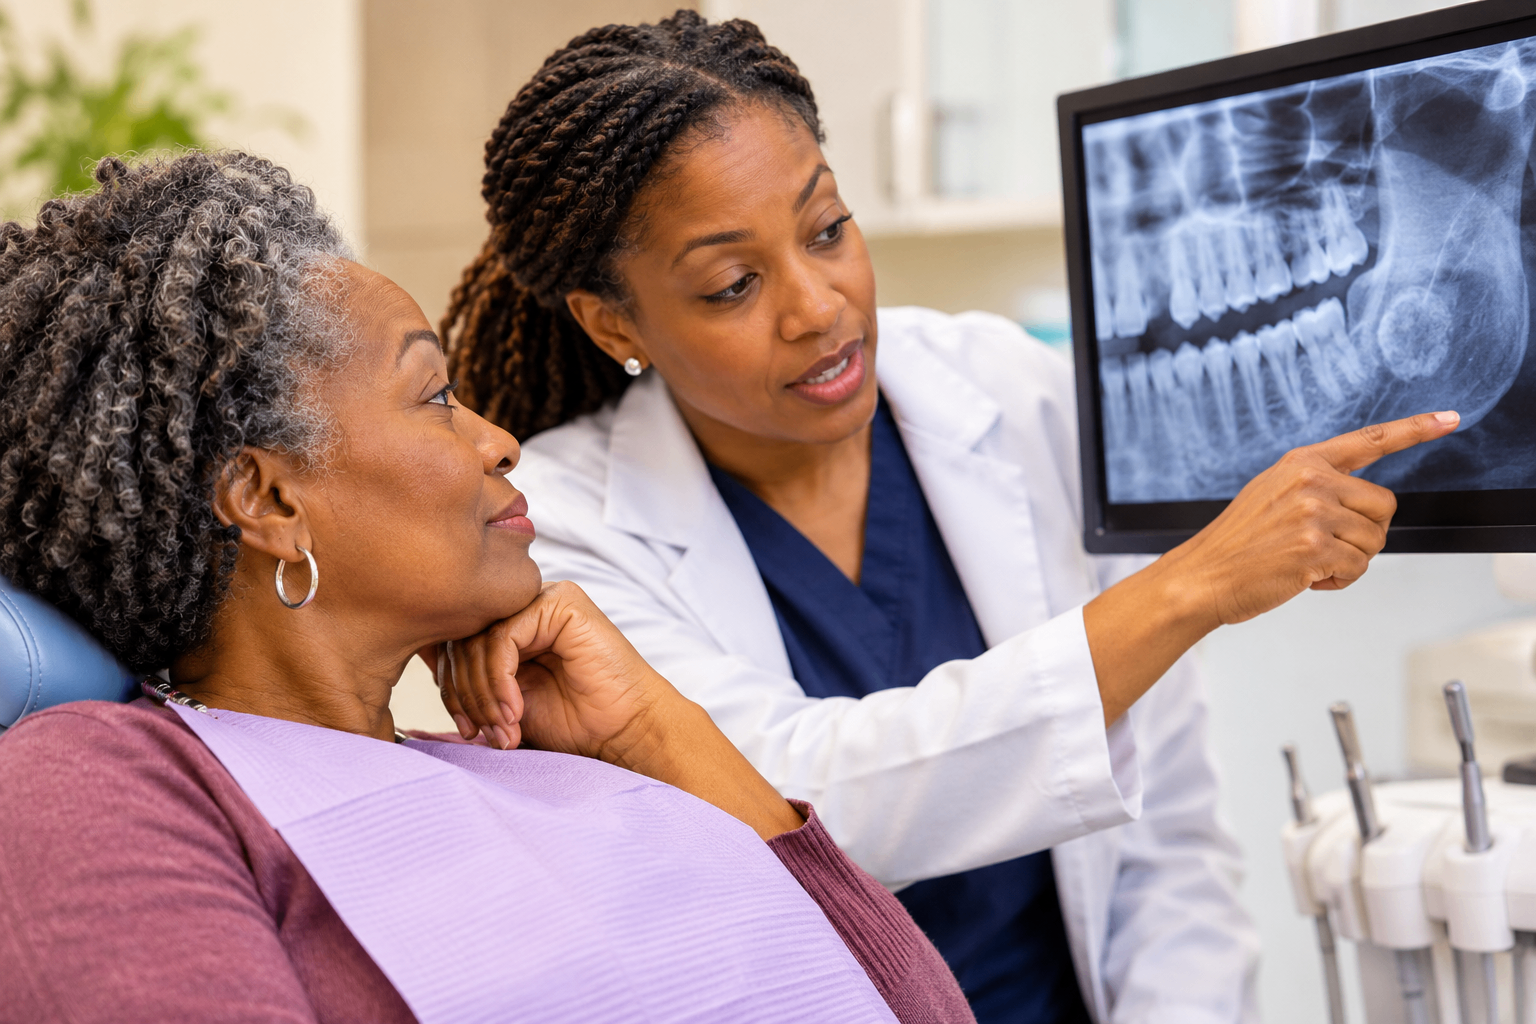
COD is most common among women in their 60s, with Black middle-aged women disproportionately represented. Because patients often don’t have symptoms, COD is often discovered incidentally during routine dental X-rays.
The jaw condition can also change appearance over time, starting as a dark area on an X-ray and gradually becoming denser and lighter as it matures.
If clinicians discover cemento-osseous dysplasia, surgery shouldn’t generally be recommended unless the area is infected. “The affected teeth are usually healthy, and that’s one of the most important clues endodontists look for,” said Randy Middleton, DDS, an endodontist at EndoConnect.
Early lesions can look similar to infections, which Dr. Middleton explained is how some patients end up getting root canals they didn’t need. Other procedures, such as extractions, biopsies, or surgery, can increase the risk of poor healing or infection because the affected bone has a limited blood supply.
“Management is generally observation, periodic imaging, and good oral hygiene,” said Ryan S. Lee, DDS, Chief Dental Officer at Community Health Connections. “Surgery is not the default.”
In its early stages, cemento-osseous dysplasia may look like an infection around the tooth roots, such as a periapical abscess, cyst, or granuloma, which often require root canals. “Check for symptoms and rule out COD first,” Dr. Lee said.
The teeth associated with COD are also usually vital, meaning the nerve tissue inside the tooth is still alive. “That’s an important difference from infections that start inside a tooth,” Dr. Middleton noted.
As COD matures and becomes denser, it can resemble other jaw conditions, such as ossifying fibroma, chronic sclerosing osteomyelitis, fibrous dysplasia, or cementoblastoma. Sometimes, patients with Paget’s disease can also show similar dental findings.
One clue to distinguish cemento-osseous dysplasia from other conditions is how it relates to the tooth and what symptoms are present. Cementoblastoma, for example, can be quite painful and is typically attached directly to the root, while COD generally isn’t. Fibrous dysplasia can be differentiated by a more ground-glass appearance, unclear borders, and expansion.
Although COD is benign, accurate diagnosis is still crucial to avoid misdiagnosis and unnecessary medical procedures.
Before starting treatment, clinicians should assess the tooth’s health and check for symptoms to rule out infection. Consider the patient’s demographics — especially since COD occurs commonly in middle-aged women and Black women — as well as location, multifocality or bilateral distribution, and how the lesion appears on the X-ray.
Because COD is often discovered accidentally on X-rays, further examination and 3D dental imaging can give clinicians a clearer picture. “Compare with prior films to see how the lesion has evolved,” Dr. Lee said. ”Typical cases are usually diagnosed by imaging alone.”
If the patient has no symptoms and the findings are consistent with COD, the best approach is to leave it alone and monitor the area. Again, avoid surgery or biopsy, as the affected bone may not heal properly and could become infected. “COD looks different as it develops, so recognizing those changes is an important part of making the diagnosis,” Dr. Middleton said.
If the lesion looks unusual or the diagnosis is uncertain, additional evaluation or referral may be necessary. “The goal is to make the right diagnosis without putting the patient through a procedure they may not need,” Dr. Middleton said
Clinicians should first test the tooth and review X-rays to understand what’s happening. “Not every periapical radiolucency is caused by an infected tooth, and assuming that can lead to unnecessary treatment,” Dr. Middleton noted.
However, if patients experience symptoms like pain, swelling, drainage, exposed bone, rapid growth, tooth displacement, or unusual changes in the surrounding jawbone, it may warrant referral to a specialist. Irregular widening of the periodontal ligament (the thin radiolucent gap between the tooth root and bone) may raise concern for malignancy. An atypical age or lesion location, or a solitary expansile lesion, could suggest ossifying fibroma.
Consider referral if a patient has any planned extractions, implants, head and neck radiation, or antiresorptive or antiangiogenic therapy for bone tumors.
If a patient shows signs of an infection originating inside the tooth, clinicians can refer them to an endodontist. But if the lesion appears unusual or the diagnosis is uncertain, evaluation by an oral surgeon, oral radiologist, or oral pathologist may be appropriate.
By subscribing, you consent to receive emails from BlackDoctor.pro You may unsubscribe at any time. Privacy Policy & Terms of Service.
Are you a healthcare professional? Register with us today!